
Hypermobility & Exercise
Why “push through the pain” is the wrong advice

Aaron Hartman MD
September 30, 2026

Subscribe
Never miss out on new content from Dr. Hartman.
A member of The Connected Path asked me this on a live call, and it’s the best version of a question I get almost every week:
I don’t tolerate exercise very well. I don’t seem to build endurance, and often feel awful after exercising. Does exercise have the same benefits even when it causes the stress of intolerance?

She isn’t asking whether exercise is good for her. She’s asking something harder: whether the thing that’s supposed to help her is the same thing that keeps knocking her down, and whether she’s supposed to keep paying that price.
The answer she’d been given, over and over, was to push through. That answer is wrong for this population, and it’s wrong in a specific and fixable way.
Movement does help people with hypermobility. It helps for a reason that has very little to do with fitness, and that reason changes what kind of movement you want and how much of it you should be doing. Most of the advice in circulation gets both of those backwards. It aims at the wrong quality, and it sets the dose by how hard something felt rather than by what it costs you the next morning.
So this article is about two things:
- What movement is doing in a loose-jointed body
- How to decide how much of it to do.
Two pieces of advice that make this worse
Stretch more

The first is to stretch more. It gets offered because you look flexible, and flexibility reads as a strength, so lengthening tissue looks like the natural direction to go.
Bone pain in hypermobility is often small micro-tears. The stretchiness causes the tear, the tear causes inflammation, and the inflammation causes the pain. Tissue that already travels farther than it should doesn’t need help traveling farther. Passive stretching asks tissue you can’t yet control to lengthen, which adds to the tearing that was already generating the pain.
Push through
The second is to push through. It gets offered because nothing obvious turns up. Those micro-tears are tiny. You wouldn’t register any one of them as an injury, and they don’t show on imaging. I’ve written about what that steady stream of tears does to your nervous system in why hypermobility makes you anxious. When the tests come back clean, the conclusion tends to be deconditioning. In other words, “you’re out of shape,” your body has lost fitness because you stopped using it, and the way out is to use it more. That conclusion carries its own prescription, which is more effort.
But for someone whose tolerance has been shrinking for years, more effort is the one input that reliably makes things worse. I’ll come back to why, because it has a mechanism and a number attached to it.
If you’ve never had the word hypermobility applied to you, or you have and it never got explained properly, start with our guide to hypermobility spectrum disorder.
What loose tissue is doing to your pain
The part that gets missed is that connective tissue is wired. Your connective tissues are packed full of nerve endings. So some of the low-grade cortisol and adrenaline spikes you get just from living, just from sitting and moving because of the looseness, come off that tissue all day long. And if you can tighten the tissues down, you can diminish that overactivation of the brain.
That’s the whole argument for movement in hypermobility, and it points somewhere other than where most exercise advice points. The goal is tissue that holds position. When tissue holds position, the alarm quiets down, and the cortisol and adrenaline that alarm was driving quiet down with it. I’ve laid out that loop in full, including what sustained cortisol does back to the tissue itself, in the anxiety article. I won’t repeat it here.
Pain isn’t only the output of that loop. It’s also an input to it. Chronic pain activates your nervous system and can cause a lot of issues, which means untreated pain is feeding the same overactivation that the loose tissue is feeding. That’s the reason I treat pain in hypermobile patients instead of asking them to tolerate it. Tolerating it keeps the loop running.
The same logic is why I put bodywork in a different category from everything else on the list. Hypermobility means nervous systems get overactive, and they tend to sit in fight or flight.
Manual, myofascial, craniosacral and visceral work reach the nervous system through the tissue, which is the route that matters when the tissue is what’s generating the signal.
- Visceral work for bowel function
- Myofascial for rib dislocation
Look for someone who does more than one of them.
Why you can be hypermobile and feel stiff
A lot of readers will have stalled two sections ago, because the description doesn’t match. You aren’t flexible. You’re actually tight. Your back hurts, and you can’t touch your toes.
I hear that in clinic constantly. There are two things going on.
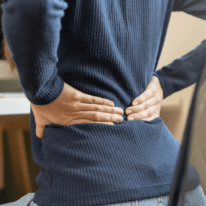
The first is history. When someone tells me they’re stiff, I ask about the past. How flexible were you when you were ten? And the answer is almost always some version of: “oh, I could put my hands flat on the ground.”
In other words, you were hypermobile. Your body spent 20–30 years compensating, and the connective tissue hardened to hold things in place. What you’re feeling now is the compensation, not the original state.
The second is happening right now, and it explains where the tightness sits. Because the muscles around a loose joint tend to be weak, the fascia tightens down to support the structure instead. So you get tightness in the big areas, the back especially, while the joints themselves stay loose. Loose at the joint, tight across the fascia, same body, same day.
This matters for what comes next. Specific exercises can relieve that tightness by strengthening the muscles, which takes the pressure off the fascia and off the joints. Stretching the fascia treats the compensation. Strengthening the muscle treats the reason the compensation exists.
What actually helps: control, not range
Strengthening the muscle so the fascia can let go is one instance of a larger idea that holds this whole section together. The goal of movement here is control rather than range.
What it means in practice is work that asks a muscle to hold a position rather than travel through one.

Pilates is the clearest example. The isometric contractions hold the joints in place and train the body to be tighter, which is exactly the direction the nerve-ending mechanism says you want to go. The best evidence for it is recent: a pragmatic trial in early 2026 of an online Pilates program built specifically for hypermobile people, 420 participants against a waitlist control, with significant improvement in hypermobility impact, body awareness and fear of movement, held at six months.1 I’ve also followed research out of professional dance companies in the United Kingdom where dancers with Ehlers-Danlos stay at professional level on Pilates-based work, which tells you the ceiling is higher than most people assume.

I’d also flag the fear-of-movement result for the study above, because by the time people reach me, movement has usually become something they brace against. My wife Becky spent five years in the middle of it. She’s written about that stretch herself.2 She would attempt 30 seconds of high-intensity intervals and then need to sleep. Not the ordinary kind of tired. Hypermobility was one of the pieces nobody had identified yet. Here’s how she describes what that did to her:
The worst part wasn’t the physical exhaustion—it was the fear. Every setback triggered a panic that I was crashing again, that I’d lose another five years. On a family trip, I tried to walk up a steep hill. Halfway up, I felt that familiar exhaustion creeping in. My body started screaming that I was near death. I fled down that hill, convinced I was about to crash for another five years.
When a trial reports that a movement program reduced fear of movement, that is what it is measuring.

Qigong and tai chi do something similar with a gentler entry. Slow contractions, cyclic movement, body weight instead of load, and a breathing practice the weight room doesn’t have. Hip, back, knee, spine. They’re gentle enough for joints that are actively flaring, which is why they’re usually where I start someone who flares.
Straight strength work, squats and leg extensions and weights, does compensate for joint looseness by strengthening the muscles around the joint. I add my own caveat to that: many people in this population can’t do that kind of exercise, and it doesn’t carry the calming effect that Qigong and Pilates do.
Yoga can be powerful here, with a condition attached. You don’t have to give up the practice. What you drop are the parts that lengthen tissue you can’t yet control, and a good instructor will do that with you.
Orthopedic physical therapy belongs here too. Hypermobility comes with weaker muscles more often than stronger ones, and I say that plainly because nobody expects it. Strengthening specific muscles tightens the joints down. There are targeted interventions for occipital headache and for shoulders that dislocate.
Two or three of those will be wrong for you and one will be right, and which one depends on what your joints will take. That sorting is what the member tool at the end of this article does.
The threshold rule
This is the part that answers the question I opened with.
What that member described has a name. It’s push-crash, and it’s common in chronic fatigue, fibromyalgia and dysautonomia. Exercise tolerance shrinks over months and years until ordinary activity does it, and a trip to the store leaves you wiped out for a day.
The approach is graded. Find your threshold, which is the amount of activity you can do without crashing. Stay under it. Increase by about 10% a week. Do nothing that causes a crash.
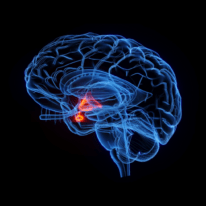
I’m strict about that last part for a reason. Every crash costs you part of your reserve. Pushing day after day doesn’t build tolerance in this population. It makes the condition worse over time. What I see behind it is the mid-brain structures, the hypothalamus and pituitary, trying to put the body into a hibernation state. None of this is new. It’s how we’ve worked with chronic fatigue patients for the last 15–20 years.
Your threshold also moves. It’s lower when you’re sicker and lower in a flare. I say this about diet and it holds here just as well: the sicker you are, the more gentle you have to be with some of these things. You can make radical changes when you’re healthier, and when you’re sicker, you have to make smaller ones.
During a flare, the flare sets the dose. With POTS I tell people to listen to their POTS. If dysautonomia and POTS are part of your picture, hypermobility and chronic health issues covers that side properly.
So to answer her directly: yes, exercise still has benefits, and no, you don’t have to buy them with the crash. The crash is the sign that the dose was wrong.
About walking

One of the four foundations I keep coming back to, and the one I wrote about at length in UnCURABLE, is that you have to activate your body and move it physically in order for everything else in your body to work the way it should. That’s a claim about what the rest of your physiology needs in order to run, and fitness has very little to do with it.
In hypermobility and gut problems I made the case that walking is treatment. Movement is what makes the bowel work, and 10,000 steps a day is the number I give. I also flagged there that some of you can’t get those steps, because the instability is in your lower body or because POTS makes upright time expensive.
If you can’t get the steps, get the motion another way. Visceral or manual therapy, or about ten minutes on a rebounder (trampoline), both move the GI tract without asking your legs to carry you for an hour. That’s a real substitute and I use it constantly.
That solves the bowel problem. The instability that took your steps away is a separate job, and a slower one.
Pain also arrives in particular shapes, and a few of them come up often enough that you should know them by name.
Where to start

Find the practitioner before you find the protocol.
- For strengthening, you want an orthopedic physical therapist who knows hypermobility. That qualifier carries the whole sentence. Most physical therapists have no idea what you’re talking about when you raise this, and the difference between one who does and one who doesn’t is the difference between a program that tightens your joints down and a program that stretches you further. The search is worth the effort.
- For bodywork, look for someone who does more than one modality, because you’re unlikely to know in advance which one your body responds to.
There’s also a conversation worth having with your doctor. If you’re being seen for degenerative disc or joint disease, you’re usually seeing a rheumatologist or a spine doctor, and what they inject is steroid.
It helps to think of this as a team instead of a referral. In UnCURABLE I describe a movement and recovery team, and for this population it usually has four seats in it. A physical therapist with advanced manual therapy training. A massage therapist working therapeutically, not for relaxation. A trainer who understands rehabilitation more than performance. And a bodyworker trained in something like craniosacral or myofascial release. You won’t assemble all of that at once, and you don’t need to. But if you know the shape of it, you stop expecting one person to cover all four.
Then start smaller than you think you need to.
Which movement is right for you depends on what your joints will take today, and that changes. You were made for health. Sometimes the first step is a smaller one than anybody told you.
If you want the wider picture, everything we’ve published on hypermobility lives in one place.
For members of The Connected Path, I’ve added a tool that does the sorting with you. You tell it what you need and what’s in your way. It takes off the table anything you shouldn’t be doing. Then it walks you through finding your own number.
References
- Russek LN, et al. “A pragmatic trial of an online Pilates program for people with hypermobility spectrum disorder and hypermobile Ehlers-Danlos syndrome.” Journal of Multidisciplinary Healthcare, February 2026. 420 participants, waitlist-controlled, with significant improvement in hypermobility impact, body awareness and kinesiophobia sustained at six months; activity level unchanged. ↩
- Hartman A. UnCURABLE: From Hopeless Diagnosis to Defying All Odds. Becky Hartman’s account, in her own words, p. 132. ↩
- Autio P, Oikarinen A, Melkko J, Risteli J, Risteli L. “Systemic glucocorticoids decrease the synthesis of type I and type III collagen in human skin in vivo.” British Journal of Dermatology, 1994;131(5):660-663. Read the study ↩